The Centers for Medicare and Medicaid Services (CMS) finalized updates to the Improving Care for Lower Extremity Joint Repair MVP for the 2026 performance year.
Although MVP reporting is currently voluntary, CMS has expressed the intention of sunsetting traditional MIPS and transitioning to MVPs entirely in the future. In the 2025 MIPS proposed rule, CMS requested feedback on the possibility of making MVPs mandatory as early as 2029.
Anatomy IT will continue to advocate for MVPs to be optional and for improvements to the Improving Care for Lower Extremity Joint Repair MVP to make it possible for all orthopedic specialists to be successful.
In this blog, we’ll break down what MVPs are, how to report them, and what changes were finalized in the 2026 MVP for orthopedic surgery.
What is a MIPS Value Pathway (MVP)?
CMS introduced MVPs as an alternative reporting option to traditional MIPS in 2023. According to CMS, MVPs aim to simplify MIPS, reduce reporting burden, and help patients make more informed decisions when choosing their clinicians.
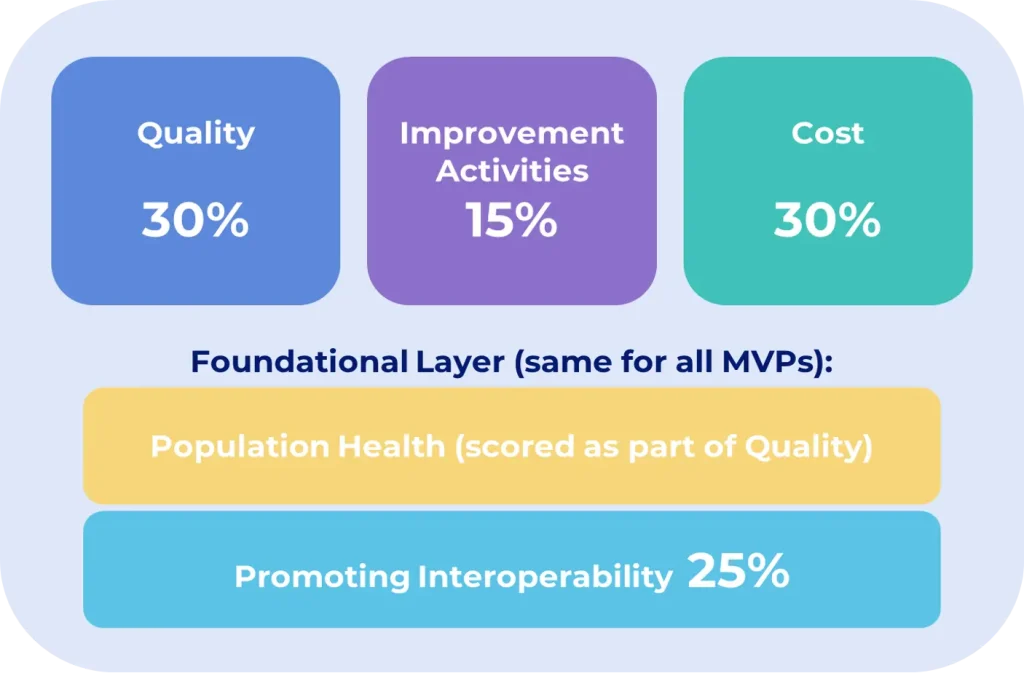
Each MVP has its own specific set of quality measures, improvement activities (IAs), and cost measures, and you are limited to those measures and activities when reporting the MVP. The Promoting Interoperability (PI) category is included as part of a “foundational layer,” meaning that PI requirements are the same for every MVP. Also included in the foundational layer is a population health measure, which contributes to your overall Quality score.
Can I Report an MVP Through a Registry?
Since 2023, Qualified Registries (QRs) and Qualified Clinical Data Registries (QCDRs), such as the American Joint Replacement Registry (AJRR), have been required to support all measures in the Quality, IA, and PI categories of the MVPs relevant to their clinicians. They are not required to support the Cost category, Population Health measures, QCDR measures, or the CAHPS for MIPS Survey.
How Are MVPs Different from Traditional MIPS?
The table below highlights the differences by category between reporting traditional MIPS versus reporting an MVP.
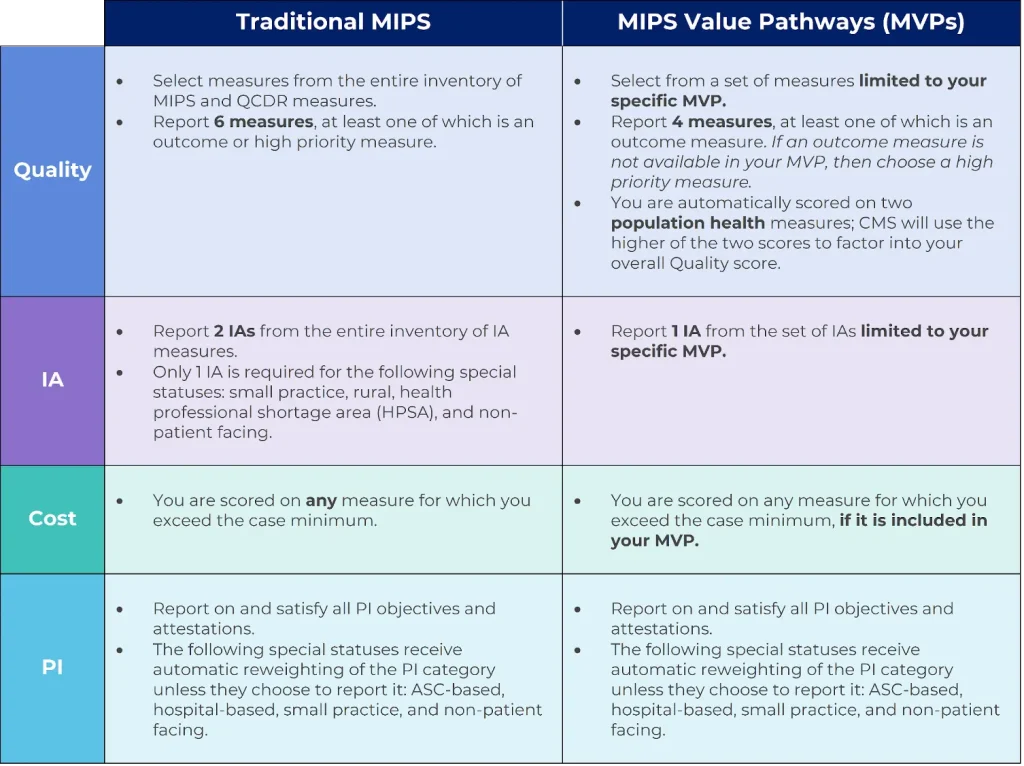
If you choose to report both traditional MIPS and an MVP, CMS will assign you the higher of the two scores.
How Do I Report an MVP?
To report an MVP for the 2026 performance year, you must register between April 1, 2026, and November 30, 2026, at 8 pm ET. Registration is available through your QPP account.
At the time of registration, you must include the following information:
- The MVP you are choosing to report,
- Any administrative claims measures you would like to be included as 1 of your 4 required Quality measures,
- Whether you are planning to count the CAHPS for MIPS Survey measure towards 1 of the 4 required Quality measures, and
- Your participation level (group, subgroup, individual, APM).
If you are reporting at the group level, you will have the chance to attest to being a single-specialty group or a *small *multi-specialty group (15 or fewer clinicians).
- If you report at the group level and are part of a large multi-specialty group (more than 15 clinicians), you are required to report at the subgroup level in 2026.
If you are an Anatomy IT client, we will discuss whether to report an MVP during your kickoff call.
What Are the 2026 Changes to the MVP for Orthopedic Surgery?
CMS finalized the following changes to the 2026 Improving Care for Lower Extremity Joint Repair MVP:
- Removed 1 quality measure:
- 487: Screening for Social Drivers of Health *
- Removed 2 improvement activities:
- AHE_9: Implement Food Insecurity and Nutrition Risk Identification and Treatment Protocols *
- PM_26: Vaccine Achievement for Practice Staff: COVID-19, Influenza, and Hepatitis B *
*These measures were also removed from traditional MIPS.
To see all the measures and activities included in the 2026 Improving Care for Lower Extremity Joint Repair MVP, click on the category names below.
Improving Care for Lower Extremity Joint Repair Measures (Specific to This MVP)
Improving Care for Lower Extremity Joint Repair MVP Quality Measures
- 24: Communication with the Physician or Other Clinician Managing On-Going Care Post-Fracture for Men and Women Aged 50 Years and Older (high priority)
- 128: Preventive Care and Screening: Body Mass Index (BMI) Screening and Follow-Up Plan
- 350: Total Knee or Hip Replacement: Shared Decision-Making: Trial of Conservative (Non-surgical) Therapy (high priority)
- 351: Total Knee or Hip Replacement: Venous Thromboembolic and Cardiovascular Risk Evaluation (high priority)
- 376: Functional Status Assessment for Total Hip Replacement (high priority)
- 470: Functional Status After Primary Total Knee Replacement (outcome)
- 480: Risk-standardized complication rate (RSCR) following elective primary total hip arthroplasty (THA) and/or total knee arthroplasty (TKA) for MIPS (outcome)
- BE_6: Regularly Assess Patient Experience of Care and Follow Up on Findings
- BE_12: Use Evidence-Based Decision Aids to Support Shared Decision-Making
- BE_26: Promote Use of Patient-Reported Outcome Tools
- CC_7: Regular Training in Care Coordination
- CC_9: Implementation of Practices/Processes for Developing Regular Individual Care Plans
- CC_13: Practice Improvements to Align with OpenNotes Principles
- CC_15: PSH Care Coordination
- PSPA_7: Use of QCDR Data for Ongoing Practice Assessment and Improvements
- PSPA_18: Measurement and Improvement at the Practice and Panel Level
- PCMH: Electronic Submission of Patient Centered Medical Home Accreditation
- MVP: Practice-Wide Quality Improvement in MIPS Value Pathways
- Elective Primary Hip Arthroplasty
10-episode case minimum
- Knee Arthroplasty
10-episode case minimum
Foundational Layer (Applies to All MVPs)
- 479: Hospital-Wide, 30-Day, All-Cause Unplanned Readmission (HWR) Rate for the Merit-Based Incentive Payment Systems (MIPS) Groups
- 484: Clinician and Clinician Group Risk-standardized Hospital Admission Rates for Patients with Multiple Chronic Conditions
All of the following attestations and measures are required (no exclusions):
- Use of CEHRT
- Actions to Limit or Restrict Interoperability of CEHRT
- ASTP/ONC Direct Review
- High Priority SAFER Guides Assessment
- Security Risk Analysis
- Provide Patients Electronic Access to Their Health Information
All of the following measures are required (unless claiming an exclusion):
- e-Prescribing
- Query of Prescription Drug Monitoring Program (PDMP)
- Immunization Registry Reporting
- Electronic Case Reporting
One of the following options is required:
- Option 1: Support Electronic Referral Loops by Sending Health Information + Support Electronic Referral Loops by Receiving and Reconciling Health Information
Exclusions are available for both measures in this option.
You can optionally report on one of the following measures for up to 5 bonus points in the PI category:
- Syndromic Surveillance Reporting
- Clinical Data Registry Reporting
- Public Health Registry Reporting
- Public Health Reporting Using TEFCA
Is Reporting the MVP for Orthopedic Surgery in 2026 Worth It?
Yes. CMS is considering making MVP reporting mandatory starting in 2029. That means there are only a few MIPS performance years left to find flaws, gather data, and recommend improvements before MVPs become the only way in which you can participate in MIPS and avoid a penalty. By reporting the 2026 Improving Care for Lower Extremity Joint Repair MVP, you will:
- Gain invaluable experience to prepare you for mandatory MVP reporting,
- Not negatively impact your MIPS payment adjustment as long as you also report traditional MIPS (even if you score poorly in the MVP), and
- Be able to provide real-world feedback to CMS to help them improve the MVP available to you before MVP reporting becomes mandatory. You can communicate with us to describe your experience with the MVP or you can tell CMS directly by commenting on the 2027 Medicare Physician Fee Schedule Proposed Rule this summer or by following the steps outlined here by CMS.
Next Steps
- Share this information with your colleagues.
- Subscribe to our blog to get alerts on this and other important issues.
You can subscribe using the field in our website footer below.
- If you are an Anatomy IT client, contact your MIPS Expert if you have any questions.
- If you are not an Anatomy IT client, contact us to learn more about our MIPS Success Plan and to reap the rewards of our combined decades of experience.
If you have any questions on this, let us know!
**

Written By: **Sarrah Hakim, MHSA
About the Author: Sarrah is the Director of Health Policy at Anatomy IT.